
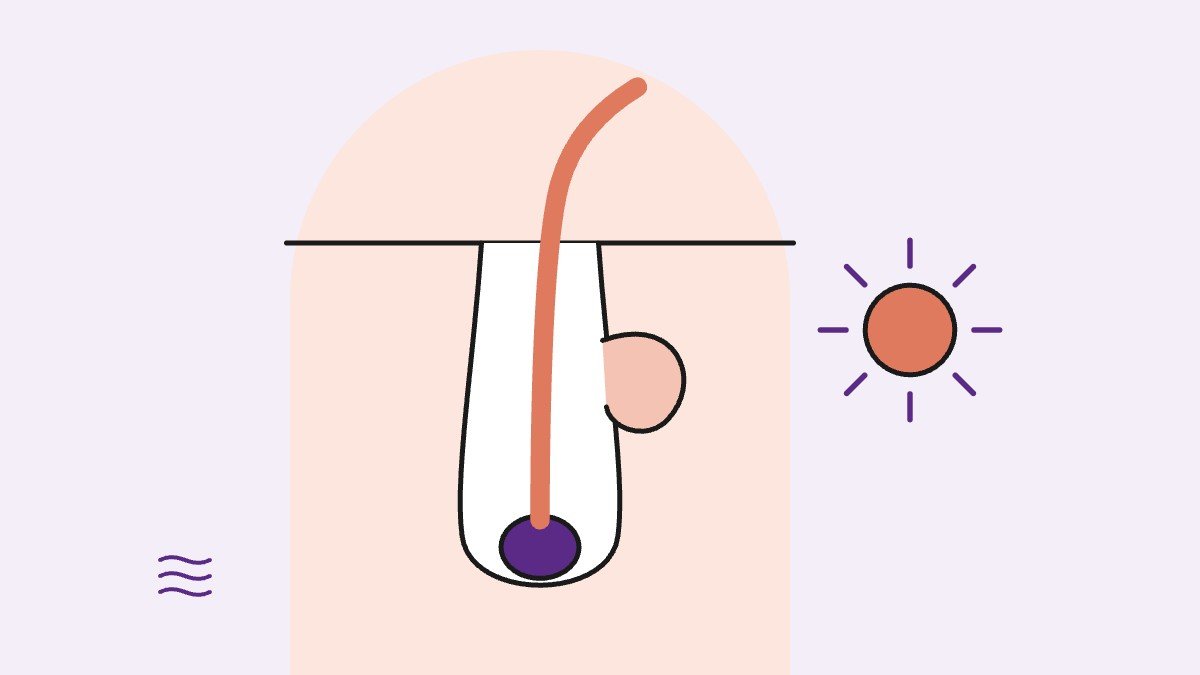
Short answer: Hirsutism is coarse, dark hair growing on a woman’s face or body in a pattern more typical of men, such as the upper lip, chin, chest, abdomen, back or thighs. It affects about 1 in 10 women. It is usually caused by androgens, hormones such as testosterone, acting on hair follicles. The most common underlying cause is PMOS (formerly PCOS). Hirsutism is not dangerous in itself, but it can be very distressing. It can be managed well with medication and hair removal.
If you have just heard the word for the first time, maybe from a doctor or after searching for why you have dark hairs on your chin, this page is a good place to start. It explains what hirsutism is, how to say it, how common it is, why it happens and what you can do about it. It also checks some popular “facts” against the evidence. Each section links to a more detailed article if you want to go further.
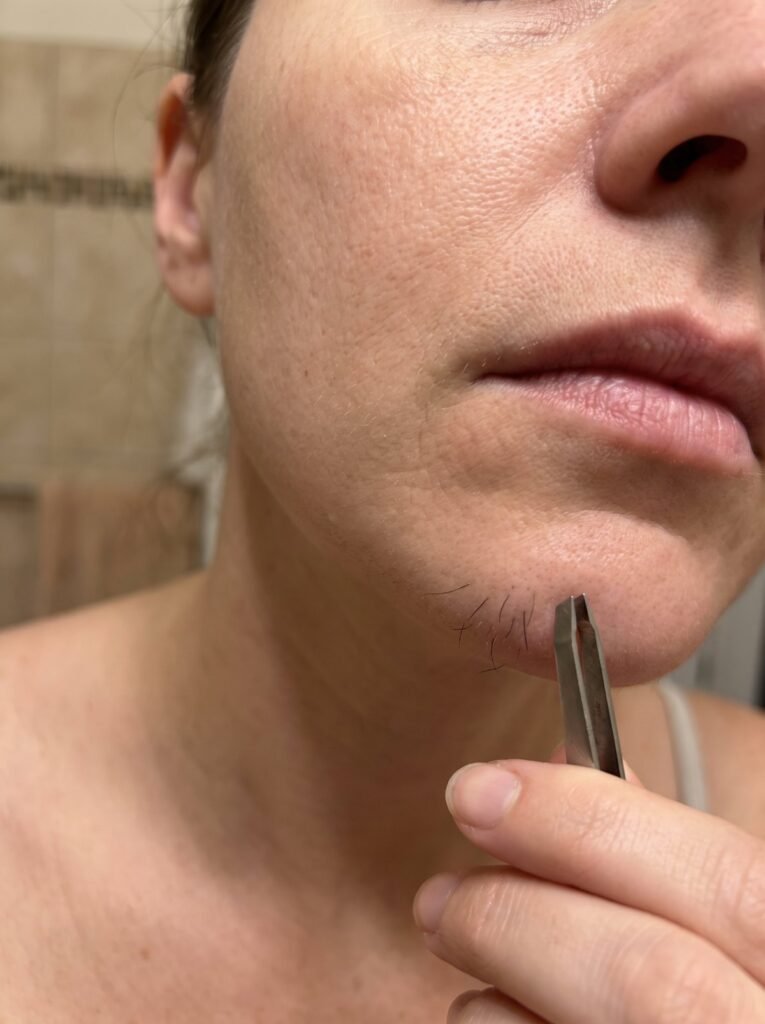
How do you pronounce hirsutism?
Merriam-Webster gives the pronunciation as HUR-suh-tiz-um (ˈhər-sə-ˌti-zəm).[1] You will also hear “hur-SOOT-iz-um”, which follows a common way of saying the related word “hirsute” (hur-SOOT).[2] Both are understood.
The word comes from “hirsute”, meaning hairy or covered with coarse, stiff hairs. It goes back to the Latin hirsutus, which is related to a verb meaning “to bristle”.[2]
What does hirsutism look like?
Most of your body is covered in vellus hair: short, fine, light “peach fuzz”. Terminal hair is longer, thicker and darker, like the hair on your scalp or in your armpits. In hirsutism, androgens cause vellus follicles in certain areas to start producing terminal hair instead.[3] These are the areas where men typically grow hair after puberty:
- Upper lip and chin, and sometimes the sideburns and neck
- Chest and around the nipples
- Upper and lower abdomen, often as a line from the belly button down
- Upper and lower back
- Upper arms and thighs
Doctors measure hirsutism with the modified Ferriman-Gallwey (mFG) score, which rates hair in nine of these areas from 0 to 4.[3] You can learn how it works, and score yourself, in our guide to the Ferriman-Gallwey score or with our hirsutism self-check.
Hirsutism vs hypertrichosis
Hirsutism is not the same as hypertrichosis. Hypertrichosis means more hair than is normal for your age, sex and ethnic background. It can cover the whole body or small patches and does not follow the male pattern. Hirsutism specifically means hair in a male-type pattern in women.[4] The difference matters because the causes and treatments are different.
How common is hirsutism?
Hirsutism is one of the most common hormone-related conditions in women. An expert consensus statement from the Androgen Excess and PCOS Society estimated that about 10% of women in most populations have it, with lower rates in women of East Asian descent.[5] Other reviews give a range of 5-15%, depending on the score used to define it.[6]
Many more women have some unwanted hair without meeting the medical definition. In a study of 633 unselected Black and White women having a pre-employment health check, about 22% had an mFG score of 3 or more. Most of these women considered themselves hirsute.[7] So if you have a few dark hairs on your chin or belly, you are far from alone.
What causes hirsutism?
Hirsutism depends on two things: how much androgen is in your blood, and how sensitive your hair follicles are to it. Inside the follicle, the enzyme 5α-reductase converts testosterone into dihydrotestosterone (DHT), a stronger androgen. This is why some women develop hirsutism even when their blood tests are normal.[3]
In a study of 950 women referred to two endocrine clinics in Italy for signs of androgen excess, the causes were:[8]
| Cause | Share of patients |
|---|---|
| PMOS (formerly PCOS) | 72.1% |
| Idiopathic hyperandrogenism (raised androgens, regular cycles, no other cause) | 15.8% |
| Idiopathic hirsutism (normal androgens and regular cycles) | 7.6% |
| Non-classic congenital adrenal hyperplasia (an inherited adrenal enzyme problem) | 4.3% |
| Androgen-secreting tumors | 0.2% |
Some medicines can also cause hirsutism, including anabolic steroids and some epilepsy medicines.[9] Hirsutism often runs in families.[6] For the full picture, including genetics, read what causes hirsutism.
Is hirsutism the same as PMOS?
No. Hirsutism is a symptom. PMOS is a condition that often causes it. The Endocrine Society estimates that 70-80% of women with hirsutism have PMOS.[3] PMOS, previously called polycystic ovary syndrome (PCOS), was officially renamed polyendocrine metabolic ovarian syndrome in 2026 after a global consensus process. The new name reflects that it affects several hormone systems and metabolism, not just the ovaries.[10] We explain how the two relate in the difference between hirsutism and PMOS.
How is hirsutism diagnosed?
A doctor will ask when the hair started, how fast it is growing, whether your periods are regular, and which medicines you take. They will then score your hair growth. The Endocrine Society guideline recommends:[3]
- An mFG score of 8 or more as the usual cutoff in Black and White women in the US and UK. The cutoff is lower or higher in other ethnic groups.
- A blood test for total testosterone in all women with an abnormal score.
- A morning 17-hydroxyprogesterone test to screen for non-classic congenital adrenal hyperplasia in women with high androgens or a high-risk background.
- No routine blood tests for women with regular periods who only have a small area of unwanted hair and a normal score.
The guideline also recognizes “patient-important hirsutism”: unwanted hair of any amount that bothers you enough to want treatment.[3] You do not need a high score to deserve help.

How is hirsutism treated?
Treatment has two goals: slowing new hair growth from the inside, and removing hair that is already there. Doctors often combine both. Whether you treat it at all is your choice. Here is an overview of the main options. Our hirsutism medication guide goes into detail.
Birth control pills
Evidence: Strong The Endocrine Society recommends combined oral contraceptive pills as first-line treatment for most women who are not trying to get pregnant. They reduce the ovaries’ androgen production. Allow at least 6 months to judge results, because hair grows in slow cycles.[3]
Anti-androgens such as spironolactone
Evidence: Strong If the pill alone is not enough after 6 months, a doctor may add an anti-androgen, a medicine that blocks androgen effects. A Cochrane review found spironolactone reduced hirsutism scores more than placebo, although most trials were small and of low quality.[3], [11] Anti-androgens can harm a developing baby, so they must be combined with reliable contraception.[3]
Laser hair removal and electrolysis
Evidence: Strong The Endocrine Society suggests laser or light-based hair removal for brown or black hair, and electrolysis for white or blonde hair.[3] A Cochrane review found that alexandrite and diode lasers reduced hair by about 50% for up to 6 months after treatment. Long-term results were not well documented.[12] Read our guide to laser, IPL and electrolysis.
Eflornithine cream
Evidence: Moderate Eflornithine cream (Vaniqa) is a prescription cream for facial hair. According to an expert consensus, applying it continuously slows facial hair growth in up to 70% of women, but the effect wears off once you stop.[5] It can also speed up results from laser treatment.[3]
Weight loss
Evidence: Limited The guideline suggests lifestyle changes for women with obesity, but notes that the effect on hair is modest.[3] In the Cochrane review, low-calorie diets lowered body mass index but did not lower hirsutism scores.[11]
Shaving, plucking, waxing, threading and hair removal creams are all safe options for day-to-day care. Natural remedies such as spearmint are popular, but the evidence is much thinner. We review them separately and say plainly where evidence is missing.
How hirsutism can affect how you feel
The Endocrine Society describes hirsutism as associated with significant personal distress.[3] If you have PMOS, the international guideline recommends that doctors screen for depression and anxiety.[13] Your feelings are valid, and talking about them, with a doctor, a counselor or others who understand, can help.
Hirsutism facts: what is true and what is not
Here are some of the most common claims about hirsutism, checked against current evidence:
| Claim | What the evidence says |
|---|---|
| “Hirsutism affects 5-10% of women.” | Roughly right. Estimates are about 10% in most populations and 5-15% depending on the definition.[5], [6] |
| “PCOS causes most hirsutism.” | True. PMOS (formerly PCOS) is behind about 70-80% of cases.[3], [8] |
| “Hirsutism runs in families.” | True. Hirsutism and the hormone conditions behind it cluster strongly in families.[6] |
| “You can have hirsutism with normal hormone levels.” | True. This is called idiopathic hirsutism and accounts for 5-20% of hirsute women.[3] |
| “Hirsutism and hypertrichosis are the same thing.” | False. Hypertrichosis is excess hair that does not follow the male pattern.[4] |
| “Laser hair removal is permanent.” | Not quite. Trials show about 50% reduction for up to 6 months. Long-term results are less certain.[12] |
| “Spironolactone can be taken on its own.” | Only with reliable contraception, because it can harm a developing baby.[3] |
| “Losing weight will get rid of the hair.” | Not proven. Diets lowered weight but not hirsutism scores in trials.[11] |
| “Treatment works within weeks.” | No. It takes about 6 months to see the effect of hormone treatment, with the full effect around 9 months.[3] |
When to see a doctor
It is worth seeing a doctor about unwanted thick, dark hair, especially if your periods are irregular or have stopped, or you also have acne.[9] Ask for an urgent appointment if:[9], [3]
- Thick, dark hair appears suddenly or gets worse quickly over a few months
- Your voice gets deeper
- Your muscles get bigger, or your clitoris gets larger
These can be signs of a rare androgen-secreting tumor, which needs prompt tests.[3] Learn more about virilization.
Frequently asked questions
Is hirsutism a disease?
Hirsutism is a sign, not a disease in itself. It usually points to an underlying hormone condition, most often PMOS, although sometimes no cause is found.[6]
Can hirsutism go away on its own?
Usually not. The most common forms tend to last for life and can become more noticeable with age.[14] Treatment can control it well. See can hirsutism be cured permanently?.
Can you have hirsutism without PMOS?
Yes. Around a quarter of women in the Italian clinic study had idiopathic hirsutism or idiopathic hyperandrogenism, and a smaller number had an adrenal condition or a tumor.[8]
How is “hirsutism” pronounced?
HUR-suh-tiz-um. “Hur-SOOT-iz-um” is also commonly heard.[1], [2]
Key takeaways
- Hirsutism is coarse, dark hair in a male-type pattern in women. It affects about 1 in 10 women.
- It is caused by androgens acting on sensitive hair follicles. PMOS (formerly PCOS) is the most common cause.
- Doctors use the modified Ferriman-Gallwey score and a testosterone blood test to assess it.
- Birth control pills, anti-androgens and laser or electrolysis are the best-supported treatments. Results take around 6 months.
- Sudden, fast hair growth or a deepening voice needs urgent medical attention.

Free: The Hirsutism Action Plan
A 12-page guide: what’s causing your hair growth, which tests to ask your doctor for, and which treatments actually work, plus a printable doctor visit checklist.
You’ll also get our weekly email. Unsubscribe anytime.
Sources
- Merriam-Webster. Hirsutism. Accessed October 2026. Link
- Merriam-Webster. Hirsute. Accessed October 2026. Link
- Martin KA, Anderson RR, Chang RJ, et al. Evaluation and Treatment of Hirsutism in Premenopausal Women: An Endocrine Society Clinical Practice Guideline. J Clin Endocrinol Metab. 2018;103(4):1233-1257. PubMed 29522147
- DermNet. Hypertrichosis. Accessed October 2026. Link
- Escobar-Morreale HF, Carmina E, Dewailly D, et al. Epidemiology, diagnosis and management of hirsutism: a consensus statement by the Androgen Excess and Polycystic Ovary Syndrome Society. Hum Reprod Update. 2012;18(2):146-170. PubMed 22064667
- Azziz R. The evaluation and management of hirsutism. Obstet Gynecol. 2003;101(5 Pt 1):995-1007. PubMed 12738163
- DeUgarte CM, Woods KS, Bartolucci AA, Azziz R. Degree of facial and body terminal hair growth in unselected black and white women: toward a populational definition of hirsutism. J Clin Endocrinol Metab. 2006;91(4):1345-1350. PubMed 16449347
- Carmina E, Rosato F, Jannì A, Rizzo M, Longo RA. Extensive clinical experience: relative prevalence of different androgen excess disorders in 950 women referred because of clinical hyperandrogenism. J Clin Endocrinol Metab. 2006;91(1):2-6. PubMed 16263820
- NHS. Excessive hair growth (hirsutism). Accessed October 2026. Link
- Teede HJ, Bahri Khomami M, Morman R, et al. Polyendocrine metabolic ovarian syndrome, the new name for polycystic ovary syndrome: a multistep global consensus process. Lancet. 2026;407(10545):2329-2339. PubMed 42119588
- van Zuuren EJ, Fedorowicz Z, Carter B, Pandis N. Interventions for hirsutism (excluding laser and photoepilation therapy alone). Cochrane Database Syst Rev. 2015;(4):CD010334. Link
- Haedersdal M, Gøtzsche PC. Laser and photoepilation for unwanted hair growth. Cochrane Database Syst Rev. 2006;(4):CD004684. Link
- Teede HJ, Tay CT, Laven JJE, et al. Recommendations From the 2023 International Evidence-based Guideline for the Assessment and Management of Polycystic Ovary Syndrome. J Clin Endocrinol Metab. 2023;108(10):2447-2469. PubMed 37580314
- DermNet. Hirsutism: excessive hair in females. Accessed October 2026. Link
This article is for education and is not medical advice. Talk to a doctor about diagnosis and treatment.