
Short answer: For most women, no. The most common causes, PMOS (formerly PCOS) and idiopathic hirsutism, are long-term conditions, and expert guidelines say treatment controls hirsutism rather than curing it. There are exceptions: hirsutism caused by a medicine, a tumor or another treatable hormone condition can go away once the cause is dealt with. Electrolysis can permanently destroy treated hair follicles, and laser can greatly reduce hair. Combining these with medication gives most women good, lasting control.
“Is there a cure?” is one of the first questions women ask after a hirsutism diagnosis. The honest answer is more nuanced than yes or no. It depends on what is causing your hirsutism and what “cured” means to you: no new dark hairs, fewer hairs, or never having to remove hair again. This article explains what is realistic, how long it takes, and which treatments have the best evidence.
Why hirsutism is usually long-term
Hirsutism happens when androgens, hormones such as testosterone, turn fine vellus hair into coarse, dark terminal hair in androgen-sensitive areas like the chin, chest and abdomen.[1] Most hirsutism comes from conditions that do not go away. Read more about what causes hirsutism.
- PMOS (formerly PCOS) causes about 70-80% of hirsutism.[1] PMOS, previously called polycystic ovary syndrome, is a lifelong hormonal and metabolic condition. It was renamed in 2026 to reflect that it affects several hormone systems and metabolism, not just the ovaries.[2]
- Idiopathic hirsutism, where hormones are normal but the follicles are more sensitive, accounts for 5-20% of cases.[1]
- Non-classic congenital adrenal hyperplasia is an inherited adrenal condition that can be managed but not cured.[3], [4]
An expert consensus from the Androgen Excess and PCOS Society states plainly that hirsutism treatment “will never be curative”, so long-term treatment is usually needed. They describe hirsutism as a chronic condition that benefits from long-term follow-up.[5] DermNet adds that the most common types persist for life and tend to become more noticeable with age.[6]
This sounds discouraging, but it is similar to many other long-term conditions: once you find the right combination of treatments, hirsutism can be kept well under control.
When hirsutism can go away
In a minority of women, hirsutism has a cause that can be removed or treated. In these cases, new hair growth can stop:
- Medicines. Anabolic steroids, testosterone and the epilepsy medicine valproic acid can cause hirsutism. So can exposure to a partner’s testosterone gel.[1] If a doctor can stop or change the medicine, the hormonal trigger goes away. Never stop a prescribed medicine without medical advice. See drugs that can cause hirsutism.
- Androgen-secreting tumors. These are rare, found in about 0.2% of women with androgen excess.[1] They are treated by surgically removing the tumor.[7]
- Other hormone conditions, such as Cushing’s syndrome and acromegaly, can cause hirsutism, and their underlying cause may be treatable.[8]
Even when the cause is removed, terminal hairs that have already formed may need direct hair removal. Treatment that lowers hormones mainly slows new growth and limits regrowth.[1]
Is hirsutism reversible?
Partly. Medicines that lower androgen levels or block their effects reduce how much hair grows, and this shows up as lower hirsutism scores in clinical trials.[9] But the effect only lasts as long as you take them, which is why expert groups expect treatment to continue long-term.[5]
Hair follicles grow in slow, unsynchronized cycles. On the face, the active growth phase lasts about 4 months. This is why it takes about 6 months to see the effect of hormone treatment, and the full effect is seen at about 9 months.[1] If you give up after 6 weeks, you will not have given the treatment a fair chance.
Treatments that control hirsutism
The Endocrine Society recommends tailoring treatment to the cause, how much the hair bothers you, and whether you want to get pregnant. Medication and direct hair removal are often combined: medication slows new growth, while hair removal clears the hair that is already there.[1] Our hirsutism medication guide covers the options in more detail.
Birth control pills
Evidence: Strong Combined oral contraceptive pills are the recommended first treatment for most women who are not trying to get pregnant.[1] The 2023 international PCOS guideline also recommends them for hirsutism in adults with PMOS.[10] In the Cochrane review of hirsutism treatments, the evidence for pills was of limited quality, but they are widely used and guideline-backed.[9]
Anti-androgens
Evidence: Strong If hair growth is still bothersome after at least 6 months on the pill, a doctor may add an anti-androgen, a medicine that blocks androgen effects.[1] In the Cochrane review, spironolactone 100 mg a day lowered hirsutism scores more than placebo, although the evidence was rated low quality.[9] Anti-androgens can harm the development of a male baby, so they must be combined with reliable contraception.[1], [10]
Eflornithine cream
Evidence: Moderate Eflornithine cream (Vaniqa) is a prescription cream for facial hair. Used continuously, it slows facial hair growth in up to 70% of women, but the effect is reversible: it wears off when you stop.[5] The Endocrine Society notes it can speed up the response to laser treatment.[1]
Metformin and weight loss
Evidence: Limited Metformin, a diabetes medicine often used in PMOS, did not improve hirsutism scores compared with placebo in the Cochrane review.[9] The PCOS guideline prefers the pill over metformin for hirsutism.[10] Low-calorie diets lowered weight but not hirsutism scores in trials.[9] A healthy lifestyle is still recommended in PMOS for metabolic health.[10]

Permanent hair removal: electrolysis and laser
This is where “permanent” comes closest to being true. Read our full guide to laser, IPL and electrolysis for practical details.
Electrolysis
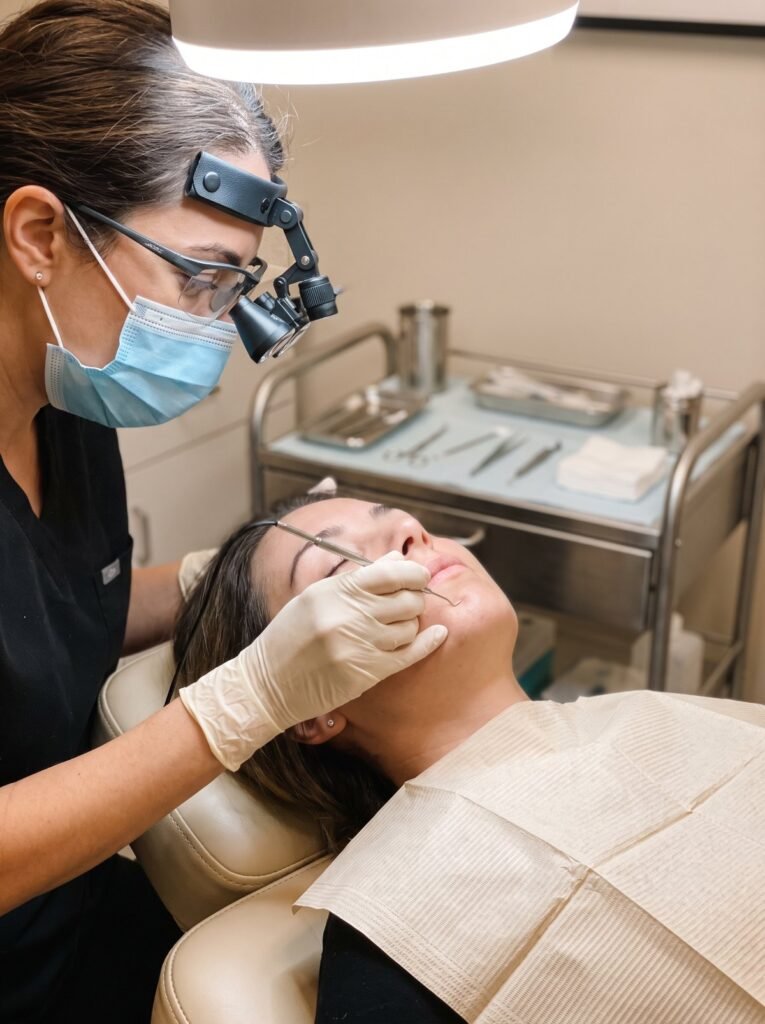
Evidence: Moderate Electrolysis passes a small electric current into each hair follicle through a fine probe. According to the Androgen Excess and PCOS Society, galvanic electrolysis, alone or “blended” with thermolysis, is the only method that may destroy the dermal papilla at the base of the follicle. This can permanently improve hirsutism in the treated area.[5] The Endocrine Society suggests electrolysis for white or blonde hair, which lasers do not treat well.[1] It treats one hair at a time, so it takes many sessions. Learn more about how long electrolysis takes to work.
Laser and intense pulsed light (IPL)
Evidence: Strong The Endocrine Society suggests laser or light-based hair removal for brown or black hair.[1] A Cochrane review of 11 randomized trials found that alexandrite and diode lasers reduced hair by about 50% for up to 6 months after treatment. No treatment was shown to remove hair permanently over the long term, and none of the trials was of high quality.[11] The 2023 PCOS guideline adds that women with PMOS may need more sessions than women with idiopathic hirsutism, and that laser works poorly on blond, grey or white hair.[10]
Because PMOS keeps stimulating follicles, the Endocrine Society suggests adding medication in women with high androgen levels to limit regrowth after laser.[1]
What “cured” can realistically look like
For most women, a realistic goal is fewer, slower-growing hairs, plus far less time spent on hair removal. A typical approach looks like this:[1]
- Find out the cause. A doctor checks your history, scores your hair and usually tests your testosterone level. You can get a first idea with our hirsutism self-check.
- Start medication if hormones play a role, usually the pill, and give it at least 6 months.
- Add an anti-androgen if needed, with reliable contraception.
- Use laser or electrolysis to clear existing hair, while medication keeps regrowth in check.
- Keep up treatment and check in with your doctor regularly.
Not everyone wants or needs all of this. Hair removal is a personal choice, and many women manage well with shaving, plucking or threading alone.
When to see a doctor
See a doctor about unwanted thick, dark hair, especially if your periods are irregular or have stopped.[8] Get an urgent appointment if:[8], [1]
- Hair growth starts suddenly or gets worse quickly
- Your voice deepens
- Your muscles get bigger, or your clitoris gets larger
- Hair keeps getting worse despite treatment
These can be signs of a rare androgen-secreting tumor.[1]
Frequently asked questions
Will my hair come back if I stop the pill or spironolactone?
Most likely, if the underlying cause is still there. Expert groups expect treatment to be long-term because it controls hirsutism rather than curing it.[5]
Can laser hair removal cure hirsutism?
Laser can greatly reduce hair, but it does not fix the hormonal cause. Trials show about 50% reduction for up to 6 months, with limited long-term data.[11] Some women need top-up sessions.
Does hirsutism get worse with age?
The most common types tend to become more noticeable with age.[6] The NHS also notes that most women get more thick, dark hair as they get older, especially after menopause.[8]
Can losing weight cure hirsutism?
There is no good evidence for this. In trials, low-calorie diets lowered weight but not hirsutism scores.[9]
Is hirsutism reversible?
Hair growth can be slowed and reduced, and electrolysis can permanently destroy treated follicles. But for most women the tendency remains, so ongoing treatment is needed.[5]
Key takeaways
- Hirsutism caused by PMOS or idiopathic hirsutism usually can’t be cured, but it can be well controlled.
- Hirsutism caused by a medicine, tumor or treatable hormone condition may stop once the cause is dealt with.
- Medication takes about 6 months to show results and works only while you take it.
- Electrolysis can permanently destroy treated follicles. Laser reduces hair by about 50% in the short term, with less certain long-term results.
- Medication and hair removal work well together: one slows new growth, the other clears existing hair.

Free: The Hirsutism Action Plan
A 12-page guide: what’s causing your hair growth, which tests to ask your doctor for, and which treatments actually work, plus a printable doctor visit checklist.
You’ll also get our weekly email. Unsubscribe anytime.
Sources
- Martin KA, Anderson RR, Chang RJ, et al. Evaluation and Treatment of Hirsutism in Premenopausal Women: An Endocrine Society Clinical Practice Guideline. J Clin Endocrinol Metab. 2018;103(4):1233-1257. PubMed 29522147
- Teede HJ, Bahri Khomami M, Morman R, et al. Polyendocrine metabolic ovarian syndrome, the new name for polycystic ovary syndrome: a multistep global consensus process. Lancet. 2026;407(10545):2329-2339. PubMed 42119588
- Carmina E, Rosato F, Jannì A, Rizzo M, Longo RA. Extensive clinical experience: relative prevalence of different androgen excess disorders in 950 women referred because of clinical hyperandrogenism. J Clin Endocrinol Metab. 2006;91(1):2-6. PubMed 16263820
- Livadas S, Bothou C. Management of the female with non-classical congenital adrenal hyperplasia (NCCAH): a patient-oriented approach. Front Endocrinol. 2019;10:366. Link
- Escobar-Morreale HF, Carmina E, Dewailly D, et al. Epidemiology, diagnosis and management of hirsutism: a consensus statement by the Androgen Excess and Polycystic Ovary Syndrome Society. Hum Reprod Update. 2012;18(2):146-170. PubMed 22064667
- DermNet. Hirsutism: excessive hair in females. Accessed October 2026. Link
- Sharma L, Kaur J. Hirsutism. In: StatPearls. StatPearls Publishing; updated May 2023. Link
- NHS. Excessive hair growth (hirsutism). Accessed October 2026. Link
- van Zuuren EJ, Fedorowicz Z, Carter B, Pandis N. Interventions for hirsutism (excluding laser and photoepilation therapy alone). Cochrane Database Syst Rev. 2015;(4):CD010334. Link
- Teede HJ, Tay CT, Laven JJE, et al. Recommendations From the 2023 International Evidence-based Guideline for the Assessment and Management of Polycystic Ovary Syndrome. J Clin Endocrinol Metab. 2023;108(10):2447-2469. PubMed 37580314
- Haedersdal M, Gøtzsche PC. Laser and photoepilation for unwanted hair growth. Cochrane Database Syst Rev. 2006;(4):CD004684. Link
This article is for education and is not medical advice. Talk to a doctor about diagnosis and treatment.